Tinnitus symptoms: know which changes need urgent help
Match the route for care to the onset and accompanying symptoms.

Describe the sound and timing
Tinnitus is hearing sound without an external source; it may be ringing, buzzing, whooshing, or another quality. Record when it began, whether it is in one ear or both, and whether it is continuous or intermittent. Note any associated hearing change, dizziness, injury, or other symptom. This history helps a clinician choose an assessment, but it is not a diagnosis of the underlying cause. Avoid repeatedly turning up headphones to test the sound. If tinnitus regularly bothers you or affects sleep or concentration, arrange a clinical discussion rather than assuming nothing can be done.
Use emergency care for specific combinations
NHS guidance says to go to A&E or call 999 for tinnitus after a head injury, or tinnitus with sudden hearing loss, facial weakness, or a spinning sensation. Do not drive yourself to emergency care. Outside the UK, use the equivalent emergency service. Give the onset and accompanying symptoms clearly when contacting help. This instruction concerns the combination of symptoms, not whether the ringing itself sounds loud. Someone with an apparently modest sound and a new urgent accompanying symptom should not wait for a routine hearing appointment simply because the tinnitus is tolerable.
Arrange urgent review for pulsatile tinnitus
If the sound beats in time with your pulse, NHS advice is an urgent GP appointment. Describe that timing plainly rather than deciding its cause from an internet recording. You can note whether the pattern is present at rest, but do not press on the neck or perform improvised maneuvers to investigate it. Keep a medicines list available for the appointment. If other emergency symptoms occur, use emergency care instead. The useful action is to communicate the pulse-linked pattern to a clinician who can decide which examination or further assessment is appropriate.
Prepare for the ordinary consultation
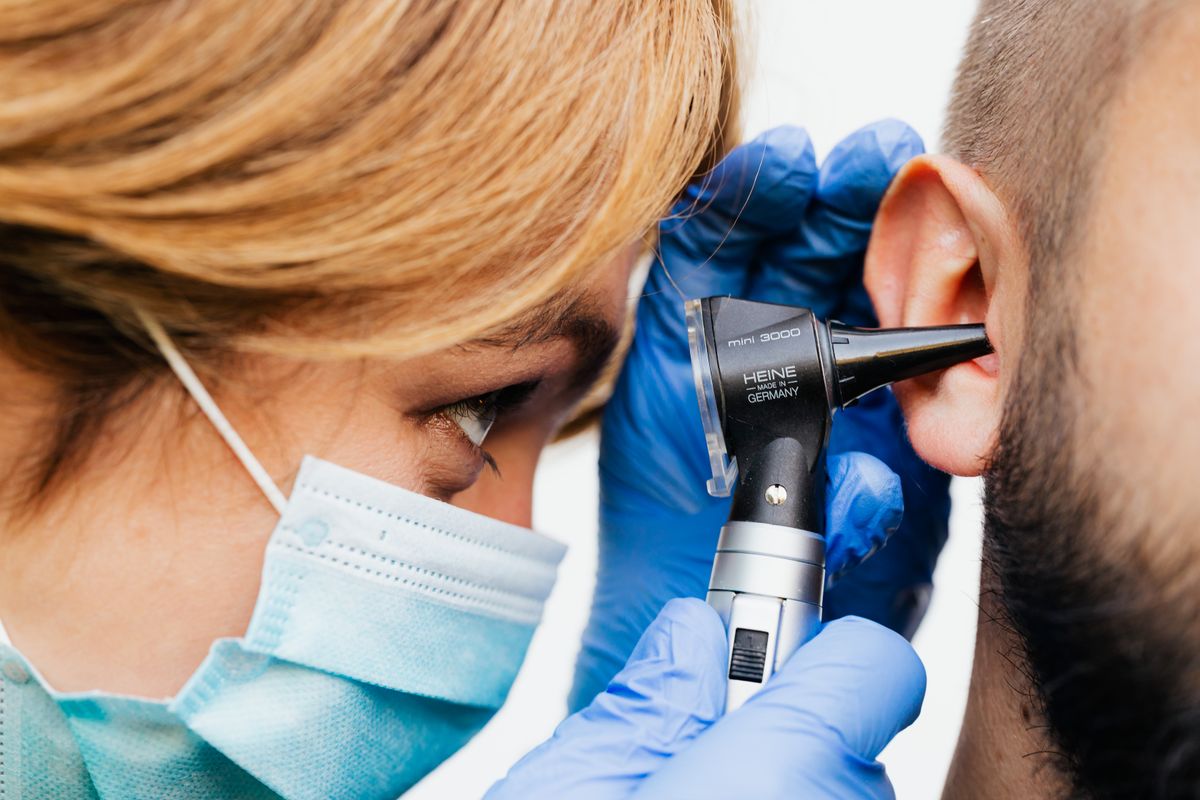
For ongoing or worsening tinnitus without those urgent combinations, book a clinical review. Bring the onset note, ear history, medicines, and a description of its impact. For example, explain that you can work during the day but struggle to fall asleep in a quiet bedroom. Ask for accessible instructions if hearing is also difficult. The clinician may examine the ear and assess hearing or arrange referral. Do not stop prescribed medicine independently because you read that some medicines can be associated with tinnitus; ask the prescriber or pharmacist to review the specific situation.
Make the next plan concrete
Ask which assessment or support is recommended, when follow-up should happen, and whom to contact if symptoms change. If a coping approach is discussed, agree on a manageable first step rather than trying many products simultaneously. Keep records of what helps sleep or daily concentration, without continuously checking the sound. Seek support if distress becomes difficult to manage. A clinical plan can address identifiable contributors and the burden of the symptom even when a simple cure is not available. The essential distinction is between urgent combinations requiring prompt help and ongoing symptoms that still deserve assessment and support.
Sources & further reading
Source links support the factual context. Practical examples and suggested workflows are original editorial guidance. Sources checked October 5, 2026.
Spotted something we should correct? Send a correction. Read our editorial policy.